Femoral hernias
Peer reviewed by Dr Toni Hazell, FRCGPLast updated by Dr Philippa Vincent, MRCGPLast updated 10 Sept 2026
Meets Patient’s editorial guidelines
- DownloadDownload
- Share
- Language
- Discussion
- Audio Version
- Add to preferred sources on Google
Medical Professionals
Professional Reference articles are designed for health professionals to use. They are written by UK doctors and based on research evidence, UK and European Guidelines. You may find the Hernia article more useful, or one of our other health articles.
What are femoral hernias?
Hernias in the groin are either inguinal or, less commonly, femoral in origin.
Inguinal hernia
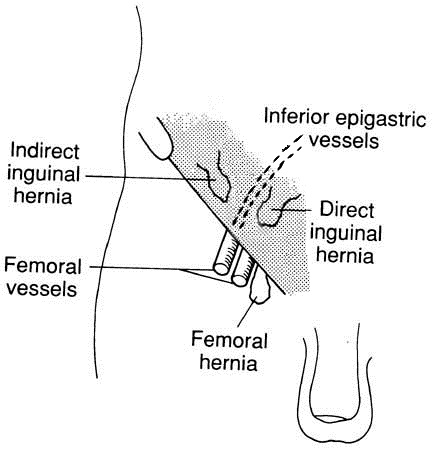
The femoral canal has the inguinal ligament as its anterior border, the pectineal ligament as its posterior border, the lacunar ligament as its medial border, and the femoral vein as its lateral border.
Epidemiology1
Femoral hernias account for only around 3% of all groin hernias. The lifetime incidence of a groin hernia is 27% to 43% in men and 3% to 6% in women.
Femoral hernias are more common in women than in men, though inguinal hernias remain the most common groin hernias in women.
The prevalence of femoral hernias increases with age, as does the risk of complications.
10% of women with a femoral hernia and 50% of men with a femoral hernia will have a co-existing inguinal hernia.
Femoral hernia symptoms (presentation)
Presentation is as a lump in the groin, lateral and inferior to the pubic tubercle. A large hernia may bulge over the inguinal ligament.
The femoral hernia often bulges more on coughing or straining, and reduces in size or disappears when relaxed or supine.
Femoral hernias are more common on the right (due to a developmental delay in closure of the processus vaginalis).
There may be a cough impulse.
Femoral hernias are more likely to strangulate than inguinal hernias.
Investigation
Diagnosis is largely clinical but ultrasound confirmation is often required before making a referral.
Imaging techniques are helpful. Ultrasound scanning is most commonly used but CT scans can be helpful in patients with incarceration or strangulation.1
Differential diagnosis
Other causes of lumps in the groin include:
Hydrocele (when differentiating from an inguinoscrotal hernia, note that it is possible to get above a hydrocele on examination).
Spermatic cord hydrocele.
Enlarged lymph node.
Psoas abscess or bursa.
Saphena varix.
Haematoma.
Femoral hernia complications
Femoral hernias are at a 12 times higher risk of strangulation than inguinal hernias.
The risk of strangulation in a femoral hernia is 22% at 3 months and 45% at 21 months.
Femoral hernias may not be noticed by the patient prior to strangulation, especially in those who have obesity.
One study reported that 45.9% of patients required femoral hernia repair as an emergency.2
If strangulation occurs, the lump may become red and tender as well as tense and irreducible. Other features include colicky abdominal pain, distension and vomiting, indicating bowel obstruction.
Femoral hernia treatment and management3
In view of the higher risk of strangulation, it is recommended that femoral hernias should be repaired; referral should be made for elective repair as soon as the diagnosis is made.4 In many parts of the UK, there is a hernia pathway which includes all femoral hernias (confirmed by ultrasound scan) but only includes other hernias that are symptomatic.
Femoral hernias may be repaired using a standard inguinal approach, an open preperitoneal approach, or a minimally invasive (laparoscopic or robotic-assisted laparoscopic) approach.15Laparoscopy does not appear to lead to more complications,67 but there is no consensus on the best approach, particularly as these often present in an acute situation and are therefore dealt with by junior surgeons.8
Emergency femoral hernia repair (for a strangulated hernia) is associated with a significantly higher risk of complications, including bowel resection, and a higher mortality than elective repairs.2
Prognosis
The mortality for elective hernia repair is low, regardless of age. However, after emergency surgery, mortality is increased seven-fold.9
Studies report that the overall operative mortality rate for strangulated hernias ranges from 1.4-13.4% but there is limited recent data.
Recurrence rates for femoral hernias are between 1 and 10%. They are more common in smokers and people with obesity, increased intra-abdominal pressure, coexisting infection, collagen tissue disorders, diabetes, and poor nutritional state.1
Chronic pain has been reported in up to 15% of people after femoral hernia repair.1
Exclusive updates for healthcare professionals
Stay informed with the latest clinical updates, professional insights, and evidence-based guidance. The Patient Pro newsletter curates essential content for healthcare professionals—delivered straight to your inbox.
By subscribing you accept our Privacy Policy. You can unsubscribe at any time. We never sell your data.
Further reading and references
- Goethals A, Azmat CE, Patel PJ, et al; Femoral Hernia.
- Humes DJ, Radcliffe RS, Camm C, et al; Population-based study of presentation and adverse outcomes after femoral hernia surgery. Br J Surg. 2013 Dec;100(13):1827-32. doi: 10.1002/bjs.9336.
- Development of an Acute Femoral Hernia Treatment Algorithm: Insights From the ACHQC National Database; I Kim et al; The American Surgeon
- Femoral hernia: Treatment delay and cause of death – A case report and an integrative review; Y Hassan et al; Muller Journal of Medical Sciences and Research
- Open Surgical Repair of Adult Inguinal and Femoral Hernias: Contemporary Techniques and Clinical Outcomes; N Subhan; Journal of Society Medicine
- Coelho JCU, Hajar FN, Moreira GA, et al; FEMORAL HERNIA: UNCOMMON, BUT ASSOCIATED WITH POTENTIALLY SEVERE COMPLICATIONS. Arq Bras Cir Dig. 2021 Oct 15;34(2):e1603. doi: 10.1590/0102-672020210002e1603. eCollection 2021.
- Incarerated femoral hernia in women – A critical view on approach options; L Pietrogiovanna et al; International Journal of Surgery Case Reports
- An Update on the Management of Femoral Hernias: Narrative Review Article; H Kumar; SAR Journal of Surgery
- Nilsson H, Stylianidis G, Haapamaki M, et al; Mortality after groin hernia surgery. Ann Surg. 2007 Apr;245(4):656-60.
About the authorView full bio

Dr Philippa Vincent, MRCGP
General Practitioner, Medical Author
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
Dr Philippa Vincent is an NHS GP working in North London.
About the reviewerView full bio

Dr Toni Hazell, FRCGP
MBBS, BSc, FRCGP, DFSRH, Dip GU med, DRCOG, DCH (London, UK, 2000)
Dr. Toni Hazell qualified from St. Mary’s Hospital Medical School and did her VTS at Northwick Park Hospital.
Article history
The information on this page is written and peer reviewed by qualified clinicians.
Article also available in English, German, Spanish, French, Italian, Portuguese, Hindi, Hebrew, Arabic, and Swedish.
Next review due: 10 Mar 2031
10 Sept 2026 | Latest version

Ask, share, connect.
Browse discussions, ask questions, and share experiences across hundreds of health topics.

Feeling unwell?
Assess your symptoms online for free
More in history and examination
- Cachexia
- Cardiovascular history and examination
- Conditions affecting the external eye
- Dehydration in children
- Dermatological history and examination
- Disease-modifying antirheumatic drugs
- Dyslexia
- Epigastric pain
- Flatulence and wind
- Genitourinary history and examination - male
- Heart murmurs in children
- Leukoplakia
- Overactive bladder
- Painful foot
- Rectal examination
- Stokes-Adams attacks
- Strabismus (squint) classification and management
- Stridor
- Thirst
- Vertigo